TRT and Fertility: How Testosterone Affects Sperm Production
TRT can reduce sperm production even when blood testosterone improves. Understand the feedback loop, hCG and enclomiphene evidence, and questions for a fertility consultation.
PeakedLabs editorial standard. We organize provider, pricing, lab-monitoring, and safety signals for research. This is not medical advice; use it to prepare better questions for a licensed clinician.

The question and the answer
Yes. Testosterone replacement therapy can reduce or stop sperm production, even when the blood testosterone result rises. The 2024 AUA/ASRM male infertility guideline advises against prescribing exogenous testosterone to men interested in current or future fertility. Discuss that goal before starting treatment, or promptly with your prescriber if your plans change while taking it.
This guide is for people with testes who are considering testosterone treatment or already using it and want to understand future biological parenthood. It explains the feedback loop and the evidence behind common alternatives; it does not select a medicine or provide a stopping, restarting or add-on schedule.
Two terms matter: endogenous testosterone is made within your body; exogenous testosterone comes from outside it, including prescribed replacement. “Endogenous” describes the source of the hormone, not proof that a treatment is risk-free. AUA/ASRM's mechanism discussion explains why externally supplied testosterone can lower the signals that support sperm production.
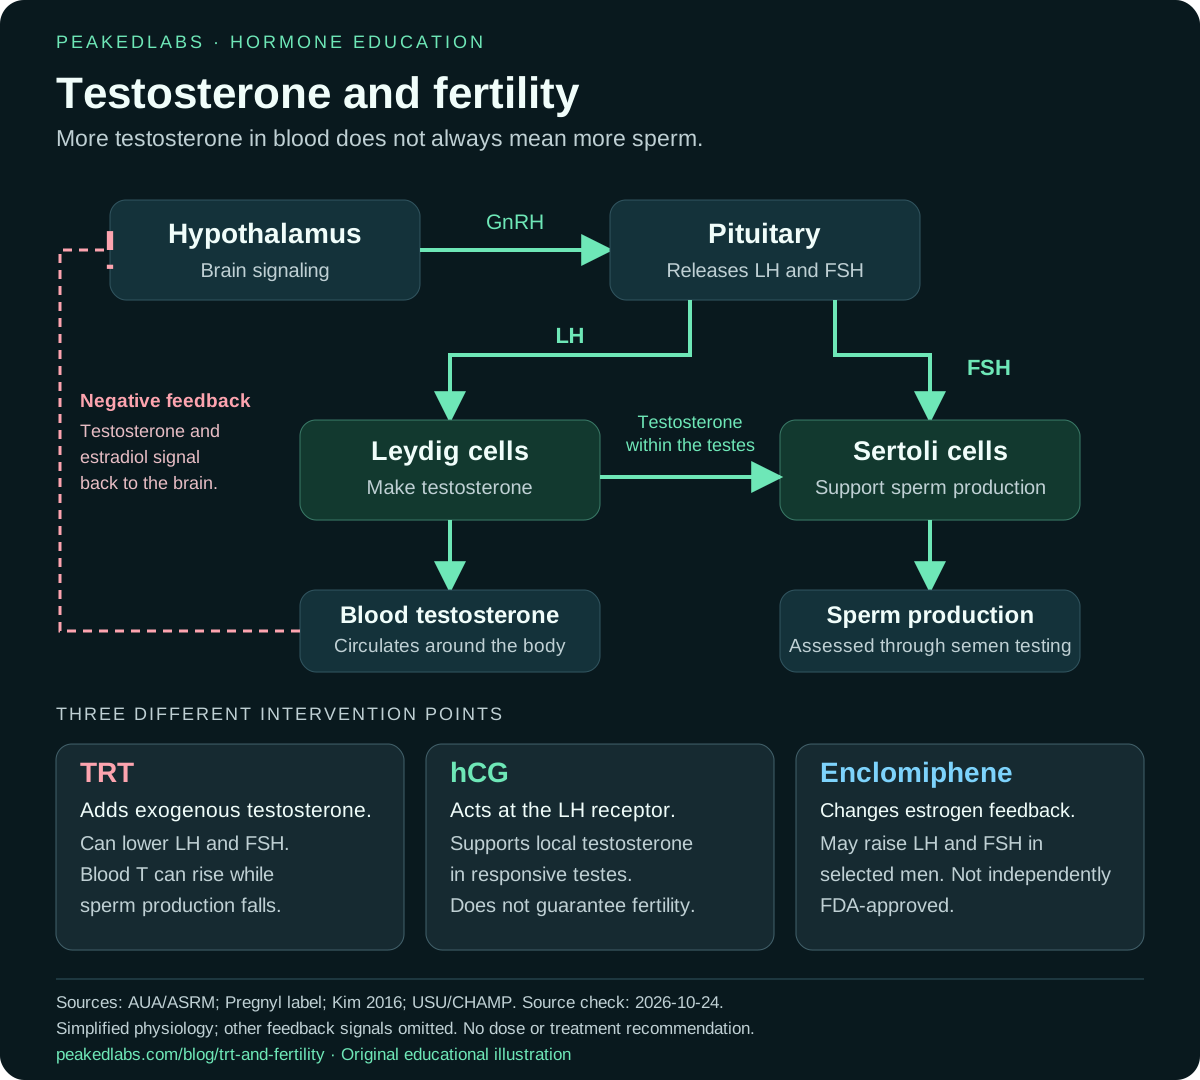
Original PeakedLabs physiology summary. It is a simplified mechanism map, not a treatment algorithm. Text equivalent appears below. Download the shareable SVG.
Free decision tools
Take the evidence to a clinician—not straight to a checkout
Use the appointment planner to organize the goal, evidence and unanswered questions. It does not assess eligibility, recommend a medicine or establish a reason to start treatment.
Want a complete place to organize the decision? The TRT Clinic Decision Kit · $29 once brings the quote comparison, appointment questions and records handoff into a printable workbook.
Preview 4 pages of the kit freeFree four-page PDF. No signup.
Preview your free decision reportCompare the evidence
| What you want to know | Evidence that helps | What it cannot establish alone |
|---|---|---|
| Is testosterone deficiency established? | Symptoms, repeat appropriately timed testosterone testing, and assessment of cause | A single low result does not settle the diagnosis |
| Is sperm being produced? | A clinician-interpreted semen analysis, repeated when appropriate | A blood testosterone result or testicular size cannot answer this |
| Could treatment affect a future pregnancy plan? | Treatment history, reproductive evaluation and the couple's timeline | A clinic's “fertility-friendly” label is not a guarantee |
| Will sperm production recover? | Individual history and follow-up semen results | A study average cannot predict your recovery date |
| Would sperm freezing be useful? | A discussion with a reproductive specialist about collection, storage and future use | Banking does not guarantee a future live birth |
Why blood testosterone and sperm production can move in opposite directions
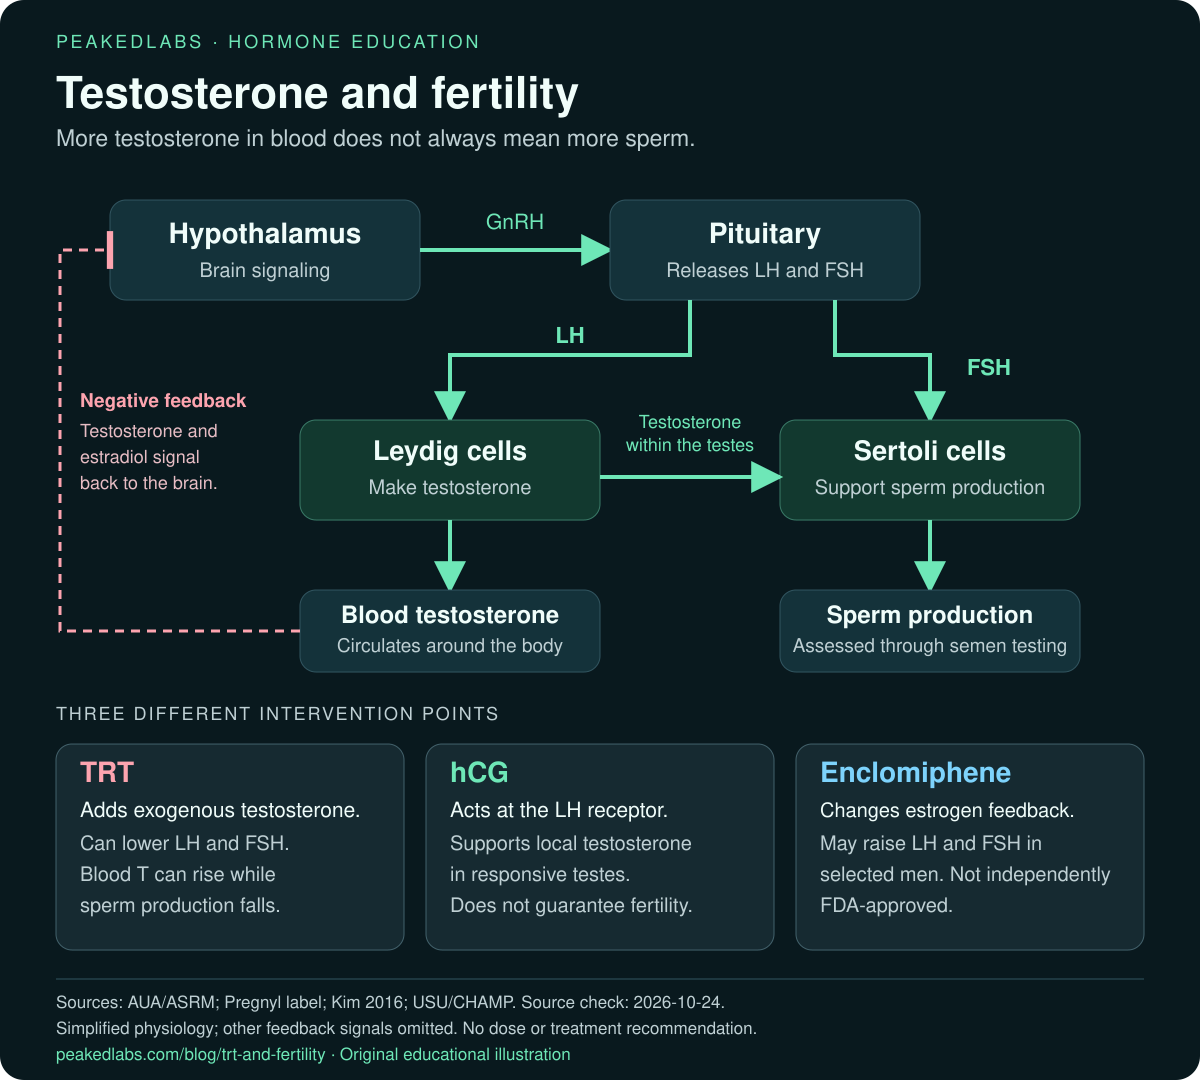
The hypothalamus releases gonadotropin-releasing hormone (GnRH), which signals the pituitary. The pituitary releases luteinizing hormone (LH) and follicle-stimulating hormone (FSH). LH supports testosterone production by Leydig cells; FSH and testosterone within the testes support the sperm-producing system.
Testosterone and estradiol participate in feedback to the brain. Adding testosterone from outside can reduce LH and FSH, so a reassuring blood result can coexist with reduced testicular testosterone production and fewer sperm. In the diagram, hCG acts at the testicular LH receptor, while a SERM such as enclomiphene acts on estrogen feedback upstream. These are different intervention points, not interchangeable ways to guarantee fertility. AUA/ASRM, Part II; Pregnyl pharmacology.
Interpretation limit: This simplified map omits other feedback signals and cannot identify the cause of an individual's low testosterone or infertility.
Questions to bring to your clinician
- What diagnosis explains my symptoms and results?
- What do my fertility plans change about the treatment discussion?
- Which result would tell us about sperm production, rather than only testosterone?
What to arrange before treatment or when fertility plans change
The Endocrine Society guideline calls for a clinical diagnosis supported by consistently low testosterone and evaluation of the cause. It recommends against starting testosterone when fertility is planned in the near term.
Bring your intended timeline, previous pregnancies or fertility treatment, medication history and original laboratory reports. Ask whether a reproductive-urology referral, baseline semen analysis or sperm-banking discussion would change the plan. If you already take TRT, explain that clearly; do not stop or add medicines from an online checklist. A specialist can discuss the medical options alongside practical questions about testing access, storage fees and who follows the results.
Interpretation limit: Having fathered a child previously does not establish current semen quality, and a clinic's intake blood panel is not automatically a fertility evaluation.
Questions to bring to your clinician
- Should I have semen testing before a treatment decision?
- Would sperm banking be relevant to my goals, and what are its limits and costs?
- Who coordinates the fertility evaluation if I am already on testosterone?
What hCG and enclomiphene evidence does—and does not—answer
hCG can stimulate testosterone production at the testes. That mechanism and selected clinical use are described in the Pregnyl label. Enclomiphene has been studied for raising the body's own testosterone while maintaining sperm concentrations relative to testosterone gel. Kim et al., 2016.
Neither finding establishes that adding hCG makes TRT reliably fertility-preserving or that enclomiphene guarantees pregnancy. Ask which outcome the proposed care is intended to change and how it will be assessed. The detailed TRT and hCG evidence review separates local testosterone from semen and pregnancy findings; enclomiphene and fertility evidence explains the endpoints used in its trials.
Interpretation limit: Treatment choice depends on the cause of the hormone problem, testicular function, the wider fertility evaluation and the time available—not a medicine label such as “natural” or “fertility-safe.”
Questions to bring to your clinician
- Does this evidence apply to my diagnosis?
- Is the expected benefit supported by semen data, pregnancy outcomes or only hormone levels?
- How will we reassess if the intended outcome does not improve?
Recovery after TRT: why there is no universal countdown
A frequently quoted 2006 analysis by Liu and colleagues followed sperm recovery after experimental hormonal contraception in 1,549 healthy men. Its endpoint was recovery to a specified sperm concentration, not conception.
Those participants and regimens do not represent every person treated for clinical hypogonadism for years. The study supports the possibility of recovery after suppression; it cannot promise a particular individual's return to baseline or provide a calendar for trying to conceive. If timing matters, ask for a plan based on your history and actual follow-up, including when to involve a reproductive specialist and how the other partner's evaluation fits.
Interpretation limit: Neither a fixed waiting period nor a rising blood testosterone value substitutes for assessment of semen and the couple's circumstances.
Questions to bring to your clinician
- What factors in my treatment history affect the uncertainty?
- How will we measure progress, and who interprets the results?
- What is the next step if the results do not support our timeline?
Put the research to use
Start with a written question list about diagnosis, fertility timing and follow-up. The free appointment planner helps organize that conversation; the decision report and optional kit organize clinic terms and costs without choosing a treatment for you.
- Download the educational diagram as a PNG for sharing (source check: October 24, 2026)
- Prepare questions for your clinician
- Organize clinic costs and questions with the free TRT decision report
- Explore the TRT Clinic Decision Kit
- Compare endogenous stimulation with testosterone replacement
- Read the hCG evidence in context
- Sources checked October 24, 2026. This is an editorial evidence review, not an independent clinical review. Historical studies keep their original dates. Primary sources: AUA/ASRM 2024; AUA/ASRM 2021 Part II; Endocrine Society 2018; Liu 2006; Pregnyl label; Kim 2016.
Frequently asked questions
Can TRT cause infertility?
TRT can suppress sperm production, sometimes to no detectable sperm in a semen sample. The effect and recovery vary. Fertility goals should be part of the prescribing discussion before treatment.
Is TRT reliable birth control?
No. Reduced sperm production is not a dependable contraceptive plan, and a testosterone prescription is not an approved male contraceptive. Discuss appropriate contraception if pregnancy is not desired.
Does adding hCG guarantee fertility on TRT?
No. Small studies support biological and semen-related findings, but they do not provide a guarantee. The reason for treatment, the fertility timeline and follow-up semen assessment matter.
Can sperm production recover after stopping TRT?
It can recover, but the timing and completeness cannot be promised from a general article. Discuss any treatment change and follow-up with the prescriber and a reproductive specialist.
Does a normal testosterone blood test mean I am fertile?
No. A blood hormone result does not measure sperm concentration, movement or the many other factors affecting pregnancy. A fertility evaluation answers a different question.
Read next
Enclomiphene vs TRT: Endogenous Production, Fertility and Evidence
The useful comparison is not “natural versus artificial.” It is how each intervention works, whom it has been studied in and which outcomes are supported.
Enclomiphene and Fertility: Sperm Counts Are Not Pregnancy Outcomes
Trials support a sperm-concentration finding in selected men. They do not establish a guaranteed pregnancy, a treatment for every cause of infertility or safety over years.
TRT and hCG: What the Fertility Evidence Actually Shows
hCG can stimulate testicular testosterone. That is a useful mechanism, but local testosterone, sperm concentration and pregnancy are separate outcomes.
The newsletter
Get the latest peptide & TRT research
Weekly evidence-based updates on protocols, costs, and telehealth provider quality.
Free forever. Unsubscribe anytime. We never sell your email.